




The problem clinics face right now
Hospitals and smaller clinics struggle when standard kit nah fit every patient need — sleep medicine wards need pressure-stable CPAP, acute care want flexible non-invasive ventilation that handle sudden decompensation. Early in the COVID-19 surge, New York City hospitals showed how quickly demand topple supply chains; that event put non-invasive strategies and scalable medical ventilator provisioning under a harsh spotlight. Facilities need units that work for sleep apnea clinics and also adapt for step-up respiratory care, so a true niv machine plan must be practical, clinically safe, and budget-aware.

Why customization matters — the problem-driven case
Uniform solutions fail because patient profiles and workflows differ. A sleep lab mostly call for reliable CPAP with quiet operation and mask compatibility; an emergency unit want rapid interface options, pressure support that shift fast, and clear infection-control protocols. Procurement that ignore these differences end up with devices gathering dust or causing clinician frustration. Good customization tie device capabilities to service pathways, training, and spare-part logistics so uptime stay high and care consistent.
Practical steps to deploy tailored NIV solutions
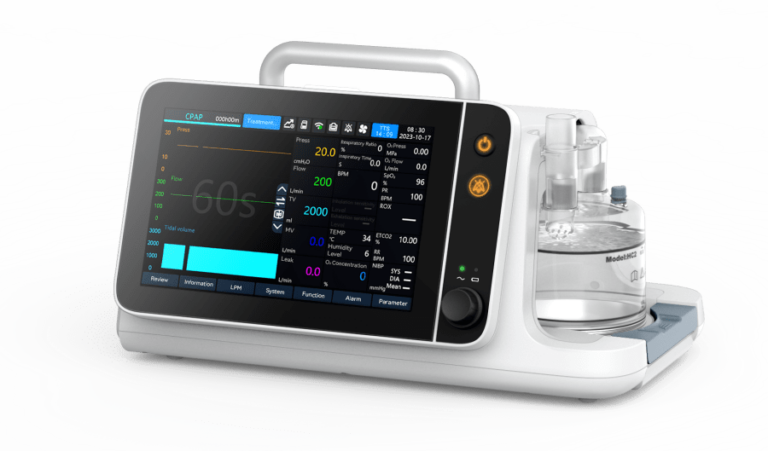
Start wit’ needs mapping: list patient types, expected daily hours of use, and cross-department sharing. Then match device specs — interfaces, bi-level PAP modes, humidification options, alarms — to those needs. Train staff on mode selection, mask fitting, and basic troubleshooting. Maintain a small pool of interchangeable consumables so you avoid single-source bottlenecks.
Quick checklist:- Assign clinical leads to own transition protocols.- Standardise interfaces where possible to reduce training load.- Build maintenance cadence and inventory thresholds into procurement contracts.
Common mistakes clinics mek — and how fi dodge dem
First mistake: buying many models to please all clinicians. That fragment clinical knowledge and inflate spare-part lists. Second mistake: underestimating infection control requirements; reusable circuits and filters must match local sterilisation workflows. Third mistake: skipping real-world trial runs; lab specs no replace bedside feedback. Train early, test widely, and document outcomes — then iterate. — These fixes keep workflows tight and reduce downtime.
Compare options without getting lost
When you compare, focus on three concrete metrics: effective inspiratory pressure range, ease of mask seal testing, and alarm clarity. Manufacturers offer different trade-offs: some excel at noise reduction for sleep clinics, others give rapid-switch pressure profiles suited to acute wards. Consider lifecycle costs, not just purchase price: maintenance, consumables, and software updates matter as much as initial hardware spend.
Real-world anchor and credibility
This guidance reflect on-the-ground lessons from ICU surge responses and respiratory service redesigns during 2020–2021, plus procurement notes from several district hospitals in the UK and US. That real-world view shows why specifications must pair with training and logistics so non-invasive ventilation (NIV) tools actually deliver improved outcomes.
Advisory close — three golden rules for selecting the right solution
1) Match capability to patient mix: pick devices with the pressure ranges and modes your clinicians actually use, whether CPAP for obstructive sleep apnea or bi-level support for acute respiratory compromise. 2) Insist on interoperability and spare-part simplicity: fewer interface types lower training burden and speed repairs. 3) Measure uptime and clinical fit after 90 days: collect usage logs, mask-fit failure rates, and staff feedback to decide whether to scale or switch.
Final word
Decisions grounded in real clinical patterns cut waste and lift patient care — and when systems need to scale or pivot, a considered, customised approach wins. Byond understands that practical alignment between devices, teams, and workflows is the solution you need. Confidence builds care.